Vertigo Treatment in Bradenton and Parrish, FL: Which Vertigo You Have, Who Treats It, and When the Neck Is the Cause
By Dr. Rusty Lavender, D.C. and Dr. Jacob Temple, D.C. — upper cervical chiropractors, Lavender Family Chiropractic, Sarasota, FL. Reviewed and updated October 2026.
Vertigo in Manatee County has a particular shape. Bradenton has one of the older populations on the Gulf Coast, and in older adults vertigo is not just miserable, it is the thing that precedes the fall that changes a life. Parrish, at the other end of the county, is young, fast-growing, and commuting, and its vertigo tends to arrive after a rear-end collision on US-301 or I-75. Both groups search for “vertigo treatment” and find the same page of physical therapy clinics, an ENT, and a general chiropractor, with no way to tell which one they need. This page sorts that out: the kinds of vertigo, who treats each in Bradenton and Parrish, what the evidence says, and where an upper cervical evaluation fits. Our complete guide to vertigo and the upper cervical spine covers the mechanism in depth; this is the Manatee County decision guide.
Educational content, not medical advice. Vertigo with a sudden severe headache, double vision, trouble speaking, facial droop, one-sided weakness or numbness, or inability to walk is an emergency. Call 911.
Vertigo After 65: The Falls Problem
About 7% of adults experience true vestibular vertigo at some point, and about 5% in any given year (Neuhauser et al., Neurology 2005). The number that matters more for Bradenton is what it does to older adults. In a national examination survey, adults with vestibular dysfunction had roughly twelve times the odds of falling, and the prevalence of balance dysfunction rose steeply with age (Agrawal et al., Arch Intern Med 2009). A hip fracture at 78 is often a vertigo story that started two years earlier and got accepted as “getting older.” It is not. Most vertigo in older adults is one of a handful of specific, treatable things, and the first job is to find out which one.
Which Vertigo Do You Have?
“Vertigo” means a false sense of movement, you or the room. The common causes feel different enough to narrow down before you see anyone.
Brief spinning when you lie down, roll over, or tip your head back; seconds to under a minute; the same every time. That is BPPV, loose calcium crystals in the inner ear, the most common cause of spinning vertigo and the one that rises most with age. It responds to a repositioning maneuver, not to medication or adjustments (Bhattacharyya et al., Otolaryngol Head Neck Surg 2017). A population study found most people with BPPV never get that maneuver (von Brevern et al., J Neurol Neurosurg Psychiatry 2007), which is the single most fixable fact about vertigo in Bradenton.
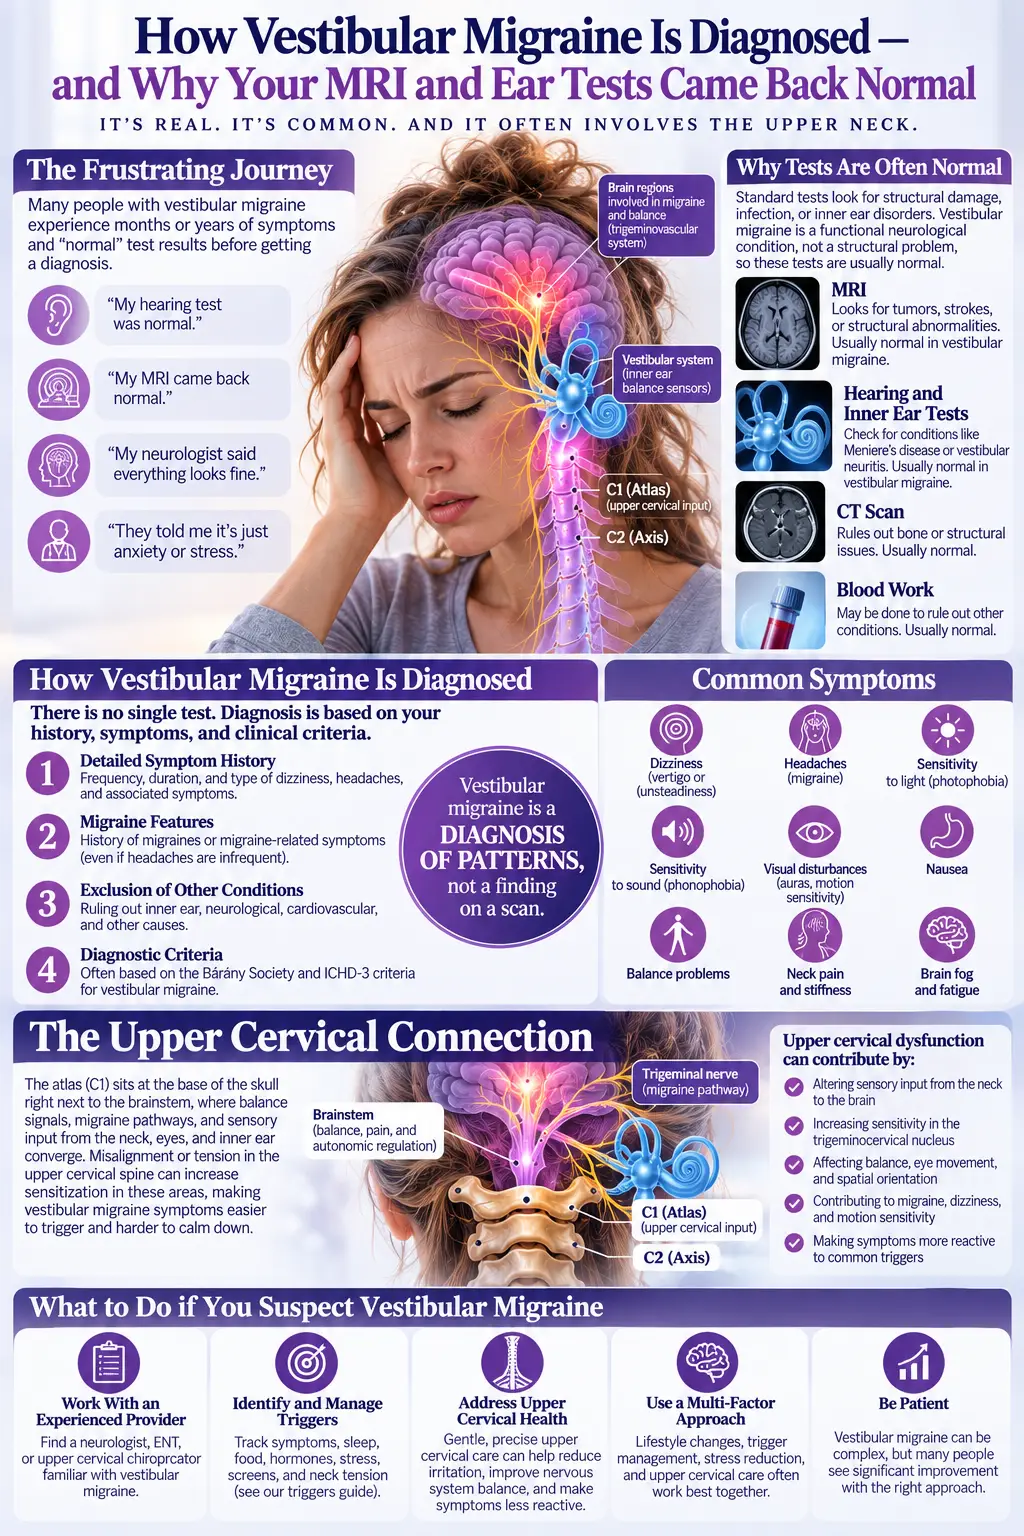
Episodes lasting minutes to hours in someone with a migraine history, often with no headache at the time.Vestibular migraine, one of the most common causes of recurrent vertigo and routinely misdiagnosed as an ear problem (Lempert et al., J Vestib Res 2012). See our vestibular migraine guide.
Attacks of twenty minutes to hours with ear fullness, roaring tinnitus, and fluctuating hearing on one side.Ménière’s disease, which needs an ENT and hearing testing; our Ménière’s guide covers where the neck fits.
Unsteadiness, floating, or spinning provoked by turning the neck or holding it in one position, with neck pain, stiffness, or headache at the base of the skull, often after a collision, fall, or concussion. Cervicogenic, neck-related, dizziness. The upper neck is one of the brain’s richest sources of head-position information, and when that signal is distorted the brain gets a report that disagrees with the ear and the eyes (Kristjansson and Treleaven, J Orthop Sports Phys Ther 2009); in whiplash patients, head-position sense measured significantly worse when dizziness was present (Treleaven et al., J Rehabil Med 2003). Our cervicogenic dizziness guide goes further.
Older adults in particular often have two at once, BPPV plus a neck component, which is why evaluation matters more than the label.
Vertigo Treatment Options in Bradenton and Parrish: Who Treats What
| If it looks like | Treatment with the best evidence | Who does it | In Manatee County? |
|---|---|---|---|
| BPPV | Canalith repositioning (the Epley maneuver), one to three visits | Vestibular physical therapist, ENT, audiologist | Yes, vestibular PT and audiology in Bradenton; PT in Parrish |
| Vestibular migraine | Diagnosis and preventive medication; vestibular therapy alongside | Neurologist | Yes, neurology in Bradenton |
| Ménière’s disease | Hearing testing, diet and diuretic management, injections or surgery if resistant | ENT / otologist | ENT in Bradenton; otology in Sarasota |
| Persistent unsteadiness after an ear event | Graded vestibular habituation | Vestibular therapist | Yes, Bradenton |
| Cervicogenic (neck-related) vertigo | Care directed at the upper cervical spine, measured before and after | Upper cervical chiropractor | No upper cervical office in Bradenton or Parrish. Closest is ours, 15–25 minutes |
Vestibular rehabilitation is well supported: a Cochrane review found moderate to strong evidence that it is safe and effective for people with a one-sided peripheral vestibular problem (McDonnell and Hillier, Cochrane Database Syst Rev2015). If your vertigo is an ear problem, a vestibular therapist in Bradenton is the right place. Medication has a smaller role than most people expect: the otolaryngology guideline specifically recommends against routine vestibular-suppressant drugs like meclizine for BPPV, because they mask the symptom, slow the brain’s own compensation, and in older adults add fall risk of their own (Bhattacharyya et al., 2017).
Where Upper Cervical Chiropractic Fits, and Where It Doesn’t
Upper cervical chiropractic focuses on the atlas and axis, the top two vertebrae, which carry most of the neck’s position sensors and sit beneath the brainstem. It is the definitive tool for the last row of the table. For the other rows it is often the missing piece that explains why standard treatment stalled: an ear or migraine problem sitting on top of a neck that keeps feeding the brain bad information.
Where it fits: dizziness provoked by neck movement or sustained positions; dizziness that travels with neck pain, stiffness, or a headache at the base of the skull; vertigo that began after a collision on US-301 or I-75, a fall, or a concussion; or vertigo that has already had the Epley maneuver or a course of vestibular therapy and is still not right. That last group is a large share of the Bradenton patients we see, and our article on when vestibular rehab isn’t working is written for them.
The evidence supports treating the upper neck in that group. A randomized trial in Physical Therapy found that gentle manual therapy directed at the upper cervical spine reduced cervicogenic dizziness compared with placebo, with the benefit still present at twelve months (Reid et al., Phys Ther 2014). Upper cervical chiropractic is the most precise way to treat that target: the correction is calculated from 3D imaging rather than applied by feel, and it is delivered without rotating the neck. What that adds is measurement: we only correct what the imaging shows, and you can see afterward whether it changed.
Where it doesn’t fit: BPPV. No adjustment moves crystals. We screen every vertigo patient with positional testing and, when the picture is BPPV, send you to a Bradenton vestibular therapist for repositioning, because that is the treatment. Our BPPV article explains what to expect.
What an Upper Cervical Evaluation Involves
The first visit is an evaluation. We take a full history of the vertigo and of every collision, fall, and head injury going back decades, because that is usually where an atlas misalignment began. We screen for BPPV with positional testing and for the signs that point to the ear, migraine, or something central. Then we measure: 3D cone-beam CT of the upper cervical spine, which shows the position of the atlas and axis in three dimensions including rotation a flat X-ray cannot show; paraspinal thermography, an objective marker of the nervous system’s pattern along the spine; and a head-repositioning test that measures how accurately your neck reports head position to your brain. We review the findings with you before any care begins. If the imaging shows a misalignment consistent with your symptoms, the correction is a precise, low-force procedure delivered to the atlas, with no twisting and no cracking, which matters for someone whose dizziness is set off by turning the head and for an older neck. If it shows nothing to correct, we say so and get you to the right next step.
Getting Here From Bradenton and Parrish
Our office is at 5899 Whitfield Avenue, Suite 107, at the corner of University Parkway and Whitfield Avenue, in Manatee County on the Sarasota line, just west of I-75. From downtown Bradenton it is about 12 miles and 22 minutes south on US-301; from Bayshore Gardens, 17 minutes; from East Bradenton near I-75, 10 to 15. From Parrish and Ellenton, about 20 miles and 25 minutes via US-301 South or I-75 South. Free parking at the door, which matters when you are dizzy. If you are not safe to drive during an episode, bring someone or wait for a clear day; evaluation does not need to happen mid-attack. Our Bradenton page and Parrish page cover who we see from each.
Who Should and Shouldn’t Come
Come for an upper cervical evaluation if: your dizziness is unsteadiness or floating rather than brief spinning; it’s provoked by neck movement; it travels with neck pain, stiffness, or a headache at the base of the skull; it began after a collision, fall, or concussion; or you have completed Epley or vestibular therapy and you’re still not right.
See someone else first if: it’s brief spinning when you lie down or roll over (vestibular PT in Bradenton for repositioning); it comes in episodes with a migraine history (neurologist); it comes with one-sided hearing change and ear fullness (ENT); or it’s new, severe, or comes with any neurological symptom (emergency department).
Frequently Asked Questions About Vertigo Treatment in Bradenton and Parrish
Where can I get vertigo treatment in Bradenton, FL? For BPPV and vestibular rehabilitation, Bradenton has vestibular physical therapy and audiology; for Ménière’s, ENT; for vestibular migraine, neurology. For neck-related vertigo, the closest upper cervical office is ours at University Parkway and Whitfield Avenue, 15 to 22 minutes from most of Bradenton.
Is there vertigo treatment in Parrish, FL? Parrish has physical therapy for BPPV repositioning. For an upper cervical evaluation, ours is the nearest office, about 25 minutes south via US-301 or I-75.
Is there a vertigo chiropractor in Bradenton? Several general chiropractors in Bradenton list vertigo. The difference with an upper cervical office is that the top of the neck is imaged in 3D before anything is adjusted, the correction does not rotate the neck, and BPPV is screened for and referred rather than adjusted.
My mother is 80 and keeps getting dizzy. Is that just age? No. In older adults it is usually BPPV, a neck component, blood pressure, or a medication, and each is addressable. Vestibular dysfunction multiplies fall risk, so it deserves a proper evaluation rather than acceptance.
Can a chiropractor help with vertigo? When the vertigo is neck-related, a randomized trial shows treatment of the upper neck reduces it, and many of our patients improve. BPPV needs repositioning, which is why we test for it first. Results depend on the cause, and we measure before care so you know what yours is.
Do you do the Epley maneuver? We screen for BPPV. When the picture is BPPV we refer you to a Bradenton vestibular therapist for repositioning; that is the right treatment, and our focus is the neck.
My vertigo started after a crash on US-301. Is that connected? Often. Dizziness and unsteadiness are among the most common symptoms after whiplash, and they track with impaired head-position sense from the upper neck. If repositioning didn’t help or there was no positional pattern, the neck is the next place to look.
How many visits will it take? We can’t say until we have evaluated you. The first visit is history, exam, thermography, and imaging if indicated, with findings reviewed before any care begins.
Can I do vestibular therapy in Bradenton and see you? Yes, and it is a common arrangement. The ear and the neck are different inputs.
Does insurance cover it? We are out of network. Many patients receive a superbill for reimbursement, and we go over costs and options before you commit to anything.
Lavender Family Chiropractic in Sarasota, Florida offers a thorough upper cervical evaluation to find out whether the top of your neck is part of your vertigo. Call (941) 243-3729 or request an appointment. 5899 Whitfield Avenue, Suite 107, Sarasota, FL 34243, on the Manatee County line.
References
- Neuhauser HK, et al. Epidemiology of vestibular vertigo: a neurotologic survey of the general population. Neurology. 2005;65(6):898–904. PMID 16186531
- Agrawal Y, et al. Disorders of balance and vestibular function in US adults: data from NHANES 2001–2004. Arch Intern Med. 2009;169(10):938–944. PMID 19468085
- Bhattacharyya N, et al. Clinical Practice Guideline: Benign Paroxysmal Positional Vertigo (Update). Otolaryngol Head Neck Surg. 2017;156(3 Suppl):S1–S47. PMID 28248609
- von Brevern M, et al. Epidemiology of benign paroxysmal positional vertigo: a population based study. J Neurol Neurosurg Psychiatry. 2007;78(7):710–715. PMID 17135456
- Lempert T, et al. Vestibular migraine: diagnostic criteria. J Vestib Res. 2012;22(4):167–172. PMID 23142830
- Kristjansson E, Treleaven J. Sensorimotor function and dizziness in neck pain: implications for assessment and management. J Orthop Sports Phys Ther. 2009;39(5):364–377. PMID 19411769
- Treleaven J, Jull G, Sterling M. Dizziness and unsteadiness following whiplash injury: characteristic features and relationship with cervical joint position error. J Rehabil Med. 2003;35(1):36–43. PMID 12610847
- McDonnell MN, Hillier SL. Vestibular rehabilitation for unilateral peripheral vestibular dysfunction. Cochrane Database Syst Rev. 2015;(1):CD005397. PMID 25581507
- Reid SA, et al. Comparison of Mulligan sustained natural apophyseal glides and Maitland mobilizations for treatment of cervicogenic dizziness: a randomized controlled trial. Phys Ther. 2014;94(4):466–476. PMID 24336477
Related Posts

Get our upper cervical articles first.
Patients Experience